
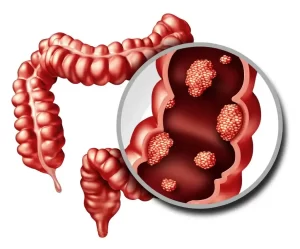
Colon & Rectal
Colon and rectal surgery, commonly known as colorectal surgery, is a broad field of medical operations used to treat various ailments that affect the lower part of the gastrointestinal tract. These diseases include colon cancer, rectal cancer, colitis, Crohn’s disease, twisting of the colon (volvulus), diverticulitis, anal fissures, hemorrhoids, rectal prolapse, and large polyps.
Polyps are growths that protrude from the inner wall of the large bowel. While not all polyps develop into cancerous tumors, an individual with polyps is usually at a higher risk for developing colorectal cancer. Some of these colorectal ailments like volvulus, result from acute symptoms that need emergency treatment procedures. Colon cancer takes a long time to get noticed as they grow gradually. A routine colonoscopy can identify colon cancer.
A screening colonoscopy is a recommendation for individuals 50 and up and those with higher risk factors. This procedure is also for individuals under 50 who are experiencing gastrointestinal bleeding. Having routine screening is essential in identifying pre-cancerous polyps removed endoscopically to prevent growing into cancerous tumors. A primary care doctor or a gastroenterologist does a routine colonoscopy. If the treatment path recommends surgery, the case gets forwarded to a surgeon.

There are several types of colorectal surgery operations;
- Colectomy - This is a removing part or all of the large colon
- Colostomy -T his involves creating an opening in the stomach wall through which stool can pass
- Endoscopic Surgery – This involves cancerous tumors using a flexible scope with a camera at the tip which enables the surgeon to operate without making significant invasive cuts
- Hemorrhoidectomy – This procedure removes hemorrhoids
- Ileal Pouch Anal Anastomosis (J-Pouch) – This procedure attaches a bag (j-pouch) to the intestines to collect stool after a colectomy
- IInflammatory Bowel Disease (IBD) Surgery – The technique used to treat ulcerative colitis and Crohn's disease
- Internal Sphincterotomy – This procedure operates anal fissures (tearing of the rectum)
- Rectopexy/resection – This procedure removes all or part of the rectum
Laparoscopic Colectomy
Laparoscopic colectomy also called a minimally invasive colectomy, involves several small incisions in the abdomen. A tiny video camera is inserted through one incision and the surgeon uses special surgical tools through the other incisions to remove the diseased areas.
Transanal Endoscopic Microsurgery
Transanal Endoscopic Microsurgery (TEMS) is a procedure performed entirely through the anus and rectum remove large rectal polyps and early-stage rectal cancer.
Laparoscopic Repair of Rectal Prolapse
Laparoscopic rectopexy is used to repair rectal prolapse. The rectum is restored to its normal position in the pelvis so that it no longer protrudes through the anus.
The colon and rectum are tasked with the removal of solid waste from the digestive tract. These organs are susceptible to several diseases among them colon polyps, colitis, Irritable Bowel Syndrome, Crohn’s disease, and colorectal cancer. Colon polyps and colorectal cancer are successfully treated using surgery. Robotic colon and rectal surgery is a minimally invasive procedure offered in situations where robotic surgeons determine the safety and benefits for patients. Like any other minimally invasive method, robotic colon and rectal surgery depend on small incisions that can minimize the rates of complications compared to open surgery or large incision.
The robot enables finer rectum dissections, considering how tight the space of their location is. Robotic colorectal surgery is a treatment option recommended for colon cancer, rectal cancer, diverticulitis, and inflammatory bowel disease. Robotic colon and rectal surgery offer various benefits over laparoscopy. It is often preferred because of the reduced rate of complications after surgery, faster recovery, less pain, and returning to work earlier. Minimally invasive robotic surgery achieves high success levels in treating these conditions because it is more accurate and able to access these organs considering their location.

The colon and rectum function can be impaired by several diseases. Colorectal surgery is prescribed for different types of diseases affecting the lower colon (sigmoid) and rectum including colon polyps, colitis, hemorrhoids, diverticulitis, inflammatory bowel disease, and colorectal cancer. Colorectal surgery removes the affected part or all of the colon and/or rectum. Diverticulitis is the most common ailment of the sigmoid colon. Other ailments include inflammatory bowel disease and hemorrhoids. The colon and rectum can also be afflicted by different types of colon and rectal cancers. The general term used for these cancers is colorectal cancer. These types of cancers are treated by removing part or all of the diseased colon or rectum. These surgical operations include Colectomy, Colostomy, Hemorrhoidectomy, Ileal Pouch Anal Anastomosis (J-Pouch), and Rectopexy.
Before surgery
The steps followed before surgery are:
- An office visit for surgical consultation where a comprehensive history and physical exam is performed.
- Completion of clinical tests for workup and staging.
- Multidisciplinary tumor board review for an expert recommendation regarding treatment strategy.
After surgery
The type of surgical procedure done determines the kind of post-surgery care required. Post care after a surgical operation involves:
- A brief admission to the ICU is sometimes required for complex procedures such as a whipple procedure. Recovery then continues in the hospital ward for another three to five days. Procedures performed robotically typically have a faster recovery and can expect discharge from the hospital one or two days earlier than after open procedures.
- The goals of postoperative care include: monitoring for and intervening on any complications that can occur, awaiting the resumption of normal bowel function, maintaining adequate hydration and nutrition, physical and occupational rehabilitation, and providing adequate pain control. Once these measures are met, the patient will be discharged from the hospital. Post-operative follow-up will be scheduled one week from discharge with Dr. Tierney.
Frequently Asked Questions About Colon and Rectal Conditions
What conditions affect the colon and rectum?
The colon and rectum remove water and salt from digested food and store waste until it is passed. They can be affected by a wide range of conditions. Colorectal cancer and polyps are the most significant, since most colorectal cancers begin as polyps that grow slowly over years. Diverticular disease, where small pouches form in the colon wall and can become inflamed, is common with age. Inflammatory bowel disease, meaning ulcerative colitis and Crohn’s disease, causes chronic inflammation. Other conditions include volvulus, where the colon twists and needs urgent treatment, rectal prolapse, anal fissures and haemorrhoids. Not all of these need surgery, and many are managed medically or endoscopically.
When should I start screening for colorectal cancer?
Current guidance in the United States recommends starting screening at age 45 for people at average risk, continuing to age 75. That is a change from the previous recommendation of 50, made because colorectal cancer has been rising in younger adults. If you have a family history of colorectal cancer or polyps, inflammatory bowel disease, or certain inherited syndromes, screening usually starts earlier and is repeated more often, and you should ask specifically what applies to you. Screening matters more here than in most cancers, because a colonoscopy can find and remove polyps before they ever become cancer. Anyone with rectal bleeding or a change in bowel habit should be assessed regardless of age rather than waiting for a screening date.
Reflects current American Cancer Society and US Preventive Services Task Force guidance. Last reviewed September 2026.
What symptoms should I not ignore?
Blood in the stool or bleeding from the back passage should always be assessed, even if you have piles, because the two can coexist and haemorrhoids are a common reason cancer is missed. Other symptoms worth acting on are a persistent change in bowel habit lasting more than a few weeks, whether looser, more frequent or constipated, unexplained weight loss, persistent abdominal pain or bloating, a feeling of incomplete emptying after passing stool, and unexplained iron deficiency anaemia. Most of these turn out to have a benign cause. The point is not to assume, since early colorectal cancer is very treatable and later disease is much less so.
Will I need a stoma?
It depends a great deal on where the problem is. For surgery on the colon itself, most people do not need one: the bowel is rejoined and that is the usual outcome. For surgery on the rectum, particularly low in the rectum, a stoma is much more likely. Sometimes it is temporary, protecting a join while it heals and reversed after a few months. Sometimes it is permanent, which is more likely when the tumour sits very low or the whole rectum has to be removed. It is worth knowing that a proportion of stomas intended to be temporary are never reversed, for reasons that vary from person to person. If a stoma is a possibility in your case it is discussed in detail beforehand, the site is marked, and a specialist stoma nurse meets you before surgery rather than after.